Referrals & Advocacy
Resources to help providers navigate referrals, support letters, and Ontario’s gender-affirming surgery process.
As a primary care provider, it is important to be an advocate for your patient and support them in actualizing their gender in all areas of their life. Your patient may seek your assistance in accessing services and supports they need. Below are resources that help you and your patient navigate systemic barriers in health, legal, and policy, including common support letters and forms.
Please note that while we recognize that indicators of gender, rather than sex, are being discussed, Ontario’s documentation consistently uses the term ‘sex designation’; thus, for simplicity, we will use this term here.
Changing Ontario Identification
All health care providers should be aware of the impact of government documentation as a social determinant of health. Trans and non-binary (TNB) people who are unable to change their name and/or sex designation on government documentation can face barriers in accessing health care, employment, housing, and income, and may be vulnerable to violence and harassment. Providers should be prepared to assist patients when they request documentation to support changes to their government identification or health card, and should ensure patients know they are willing to provide this information when needed.
There is no required order for changing documents, but Rainbow Health Ontario recommends starting with provincial identification, particularly an Ontario birth certificate if applicable, since these documents can be used to change federal identification more easily. Patients not born in Ontario should generally start by obtaining a birth certificate from their province or country of origin.
For more information, see Rainbow Health Ontario’s Trans Health Knowledge Base.
Ontario Health Cards
As of 2016, sex designation is not displayed on Ontario health cards. It should be noted that sex designation remains part of the information associated with the card in the Ministry of Health’s database. If an individual has already changed the sex designation on their Canadian Citizenship document or other OHIP-eligible document, they can use that document to change their OHIP sex designation. Alternatively, the applicant can write a declaration along with the letter from their primary care provider to support the change of OHIP sex designation.
Support Letters
Inquiring around how transitioning may influence the vocational or educational situation of the patient is important, as providers can help the patient develop strategies for dealing with gender transition in school or the workplace. Unfortunately, it is not uncommon for transition to result in the loss of a job or struggle in an academic setting.
Exceptional Access Program
Patients covered by the Ontario Drug Benefit (ODB) program include those on Ontario Works (OW), the Ontario Disability Support Program (ODSP), seniors >65 years of age, youth <24 years of age without private insurance (via OHIP+) and those on the Trillium Drug Program. For patients on ODB, injectable testosterone is covered with the submission of an Exceptional Access Form (EAP), while anti-androgens and estradiol are covered without the need for EAP approval.
Recommendation: Injectable testosterone is funded by the Ontario Drug Benefit (ODB) program for gender affirmation with an Exceptional Access Program (EAP) request. We suggest that providers submit EAP requests for both testosterone cypionate and testosterone enanthate, so that delays in access do not result when one formulation is on back order or not locally available.
Process for Gender Affirming Surgery
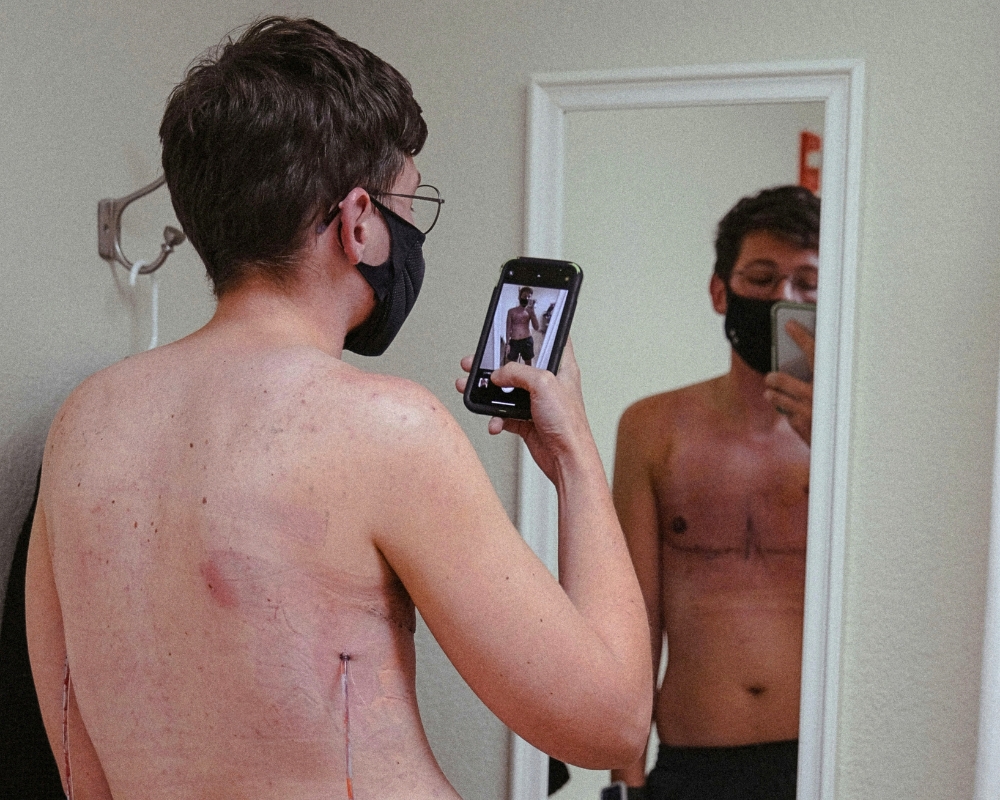
This section provides a brief overview of the Ontario system for gender affirming surgery (GAS) planning visit(s) and referral. It is not exhaustive nor intended as training for conducting GAS planning visits.
On March 1, 2016, the Ontario Health Insurance Plan (OHIP) changed the funding criteria for gender affirming surgery to align with the World Professional Association for Transgender Health (WPATH)’s 2011 Standards of Care (Version 7). This allows qualified healthcare providers to assess and refer patients for surgery, and to apply for OHIP covered funding for these surgeries.
GAS Planning Visits
Historically, the term “surgical assessment” was used to describe visits between the patient and provider where gender affirming surgery was discussed. We use the term “gender affirming surgery planning visit” to describe the collaborative approach of the visit.
The benefits of GAS referral coordination in primary care include:
- Depathologizing gender diversity
- Recognizing the relationships that are built in primary care over time
- Allowing for increased access, particularly for rural and remote TNB patients with limited access to travel
OHIP-Funded Procedures
- Vaginoplasty (includes penectomy, orchidectomy, clitoroplasty, and labiaplasty)
- Phalloplasty (includes vaginectomy, urethroplasty, glansplasty, +/- penile and testicular implants)
- Metoidioplasty (includes vaginectomy and urethroplasty)
- Clitoral release +/- vaginectomy
- Scrotoplasty with testicular implants
- Hysterectomy +/-
- Salpingo-oophorectomy
- Orchidectomy
- Mastectomy* (includes removal of breast tissue, excess skin, and proper positioning of nipple and areola)
- Breast Augmentation (has strict criteria: must have completed 12 months of hormone therapy with no breast enlargement)
* OHIP will only cover the mastectomy. Any additional masculinization (i.e., chest contouring via liposuction) must be paid by the patient and will vary from surgeon to surgeon.
Referral Process
|
Step 1 — Starting the Process
|
Step 2 — GAS Planning Visit(s)
|
Step 3 — Prior Approval
|
Step 4 — Referral to Surgeon |
|---|---|---|---|
|
The patient wants information about GAS or has decided they want GAS. The patient and provider then decide on GAS planning visit options. |
The patient is in primary care with one or more qualified providers; OR the patient is referred to psychiatry, endocrinology, or another qualified provider; OR a combination of the above is used. |
A qualified provider completes the Prior Approval Form and sends it to the Ministry of Health; an approval/funding letter is then received. |
GAS referral letters are sent to the surgeon. |